The World Health Organisation (WHO) has said about one million people die every year from bacterial antimicrobial resistance (AMR), warning that the growing threat requires stronger action across human health, agriculture, food systems and the environment.
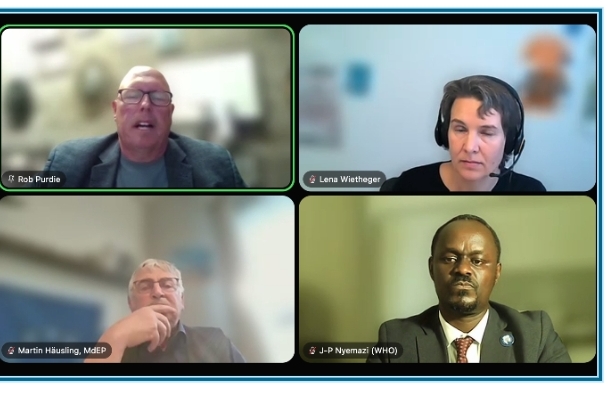
Acting Director of the WHO Department of Antimicrobial Resistance, Dr Jean-Pierre Nyemazi, disclosed this at a press conference held to mark the exhibition, “AMR: The Human Stories Behind a Silent Pandemic,” at the European Parliament in Brussels.
The exhibition, organised by the WHO and Member of the European Parliament, Martin Häusling, runs from September 28 to October 2, 2026, and features personal stories of people affected by AMR across Europe.
Nyemazi said drug-resistant pathogens were moving across borders and between humans, animals and the environment, making a coordinated One Health response essential.
“AMR is taking many lives. One million people die every year due to drug-resistant bacteria alone – that is, two people every minute die of bacterial AMR,” he said.
He said the impact of AMR extended beyond deaths, noting that resistant infections increase healthcare costs, prolong hospital stays and can force family members to abandon their jobs to care for affected relatives.
According to him, governments must back national AMR commitments with legislation, financing and accountability, while parliamentarians have a critical role in ensuring that policies translate into action.
Nyemazi also called for stronger prevention measures, including vaccination, infection prevention and control, water, sanitation and hygiene, improved animal husbandry, responsible antimicrobial use, better surveillance, access to quality medicines and diagnostics, and reduced environmental contamination.
He said WHO Member States approved an updated Global Action Plan on AMR at the World Health Assembly in May 2026, providing a framework for tackling the problem over the next decade through a One Health approach.
He added that the revised plan places greater emphasis on prevention, governance, behavioural change and measurable targets, while bringing together the four organisations under the Quadripartite partnership, WHO, the Food and Agriculture Organisation, the United Nations Environment Programme and the World Organisation for Animal Health.
Nyemazi said a 10 per cent reduction in AMR was achievable through measures such as infection prevention and control, vaccination and improved access to quality antimicrobials.
‘Stop indiscriminate antibiotic use in animals’
Häusling, who hosted the exhibition, called for an end to indiscriminate and preventive use of antibiotics in livestock, particularly practices in which entire groups of animals are treated when only one is sick.
He said the widespread use of broad-spectrum antibiotics in both human and animal health was contributing to the problem.
“When one chicken becomes sick, the entire group is given antibiotics even if the others show no symptoms. We have to move away from this mass treatment,” Häusling said.
He also warned about the environmental consequences of antimicrobial use, citing wastewater from slaughterhouses as a potential route through which drug-resistant pathogens can enter the environment and expose people.
Häusling said last-resort antibiotics, which are needed when other treatments fail, should not be routinely used in food-producing animals.
He said greater political attention was needed because AMR could affect anyone, regardless of socioeconomic status or location.
“AMR can destroy families and livelihoods. I will do everything in my power to keep this issue on the parliamentary agenda,” he said.
Survivor recounts 13-year battle with resistant fungal infection
An AMR survivor and member of the WHO Task Force of AMR Survivors, Rob Purdie, used his experience of a resistant fungal infection to illustrate the human and economic consequences of delayed diagnosis and limited treatment options.
Purdie said his illness began in January 2012 with what initially appeared to be a headache and was later diagnosed by two doctors as a sinus infection.
After treatment with two different courses of antibiotics failed, an ear, nose and throat specialist ordered an X-ray and determined that he did not have a sinus infection.
Purdie said his condition continued to deteriorate until he developed severe headaches, nausea and vision problems. He eventually went to an emergency department, where a lumbar puncture led to the diagnosis of fungal meningitis on February 14, 2012.
He said the delayed diagnosis resulted in prolonged treatment, hospitalisation and significant financial costs.
Purdie, who was diagnosed with valley fever, or coccidioidomycosis, said several antifungal medicines subsequently failed to control the infection, forcing doctors to resort to a combination therapy that included amphotericin B.
He said the treatment caused severe side effects and that he later developed squamous cell carcinoma, requiring the removal of several cancerous growths.
Purdie said the illness also affected his ability to work, leaving him unable to earn a living for about five years while he was supporting his wife and two children.
“I will not be able to retire,” he said, adding that more than a decade after the initial infection, he remains on daily antifungal medication.
He urged stakeholders to remove the word “silent” from the description of AMR, arguing that the experiences of survivors should form a central part of the global response.
WHO calls for stronger regulation of antibiotic sales
Responding to questions about antibiotic access, Nyemazi said the problem was not limited to countries where medicines could be obtained without prescriptions.
He said that in parts of sub-Saharan Africa, including Nigeria, access to even a prescription can be difficult because families often go directly to pharmacies when a child becomes ill.
He called for governments to strengthen
primary healthcare systems so patients could obtain timely diagnosis, prescriptions and appropriate treatment.
Nyemazi also urged authorities to enforce regulations restricting the dispensing of reserve antibiotics without prescriptions.
He said pharmacies should be held accountable, while digital systems could be used to track medicines dispensed and determine whether they were provided for legitimate clinical reasons.
He stressed that public education was equally important, saying people needed to understand the dangers of seeking antibiotics directly from pharmacies without proper diagnosis.
“Governments must strengthen services, the public must be educated to change care-seeking behaviour, pharmacies must be informed and held accountable, regulations must be enforced, and technology should be used,” he said.
Nyemazi also called for greater investment in veterinary services, particularly in countries where access remains limited.
He said civil society and the private sector, which plays a major role in providing healthcare in Nigeria, must also be involved in the AMR response.
According to him, poor coordination among stakeholders remains one of the biggest obstacles to tackling AMR because the problem cuts across multiple sectors.
He also called for continued investment in new antibiotics, antifungals, phage therapy, diagnostics and other technologies, while stressing that new medicines alone would not solve the problem.
“If we develop new drugs without preserving the ones we already have, the pace of innovation will never keep up with the need,” Nyemazi said.
Purdie similarly called for better stewardship of existing medicines, noting that the development of new antifungal medicines could take decades.
He said unnecessary prescriptions could be reduced immediately through better diagnosis, vaccination, responsible prescribing and public education.
The WHO has announced “One Health, One Action, Prevent AMR Now” as the theme for this year’s World AMR Awareness Week, scheduled for November 18 to 24.